This guide explains how “Drf Crefito” and “Crefito” concepts are applied in clinical practice, emphasizing diagnostic reasoning, documentation quality, and patient safety. Objectively, these terms relate to joint-related auditory or tactile findings and how clinicians record them. The article then offers a structured comparison framework and practical decision steps.
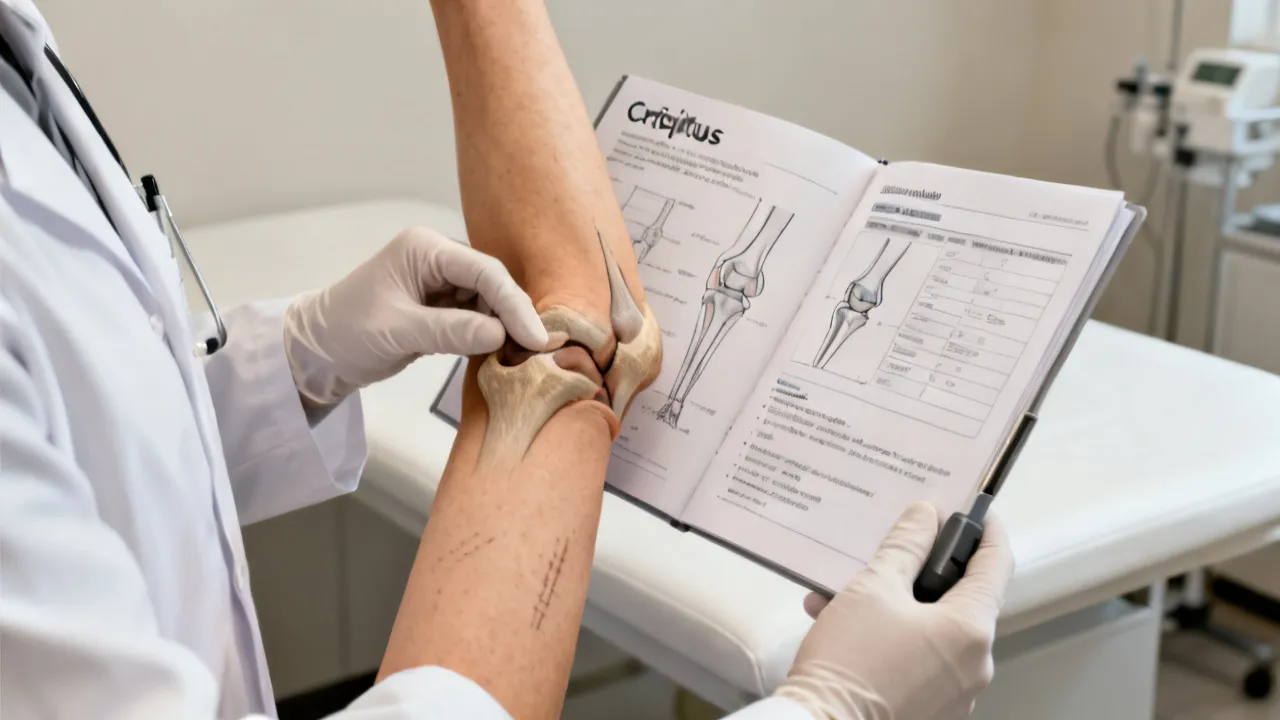
Drf Crefito is discussed here as a practical framework for how clinicians interpret and document crepitus (Crefito)—commonly described as joint “grinding,” “crackling,” or tactile-auditory phenomena—within an evidence-based assessment workflow. The goal is to support consistent examinations, reduce diagnostic ambiguity, and improve communication across care teams through clear criteria, standardized notes, and appropriate follow-up.
In many clinical contexts, Crefito is used to denote crepitus, a phenomenon patients may describe as cracking or grinding, and clinicians may detect during movement through both listening and palpation. Although the exact spelling can vary by language, the underlying clinical idea is consistent: movement of joints can produce audible or tactile signals, which may correlate with degenerative changes, altered mechanics, inflammation, or other musculoskeletal conditions.
Drf Crefito commonly appears as a shorthand used in care settings to structure assessment documentation and decision-making around those findings. From an expert perspective, the value is less about the label itself and more about the method: capturing when the phenomenon occurs, how it behaves across range of motion, what it accompanies (pain, stiffness, swelling, instability), and whether it aligns with likely clinical hypotheses.
Experienced clinicians rarely treat crepitus as a standalone diagnosis. Instead, they consider it one data point among many. In practice, Drf Crefito approaches tend to emphasize that the very clinically actionable information includes:
That broader lens improves decision quality—especially when patients present with complaints that can overlap across conditions such as osteoarthritis, tendinopathies, meniscal issues, bursitis, or post-traumatic irregularities.
Crepitus becomes more meaningful when it is accompanied by other findings. In expert practice, Crefito is interpreted through a triad:
For example, a patient who reports crepitus without pain may not require the same immediacy as someone with painful crepitus plus restricted movement or night pain. The clinician’s job is to assess probability and urgency rather than rely on the phenomenon alone.
A practical Drf Crefito-style workflow can be summarized as “observe, quantify, correlate, and plan.” The objective is to produce a record that another clinician can interpret without needing to guess what you saw.
Observe: Note whether the phenomenon is audible, tactile, or both; identify the joint and side; document whether it occurs with specific movements (flexion/extension, rotation, weight-bearing, overhead activity).
Quantify: Describe intensity using a consistent scale in your facility (even a simple ordinal description such as “mild/moderate/severe” can be more helpful than vague wording). Record range of motion and whether crepitus appears before pain or after.
Correlate: Link findings to symptoms and functional impact. Ask targeted questions (e.g., “Does it hurt during the same phase of motion each time?” “Any episodes of catching or locking?” “Is there swelling after activity?”).
Plan: Decide on conservative management versus further evaluation. Consider imaging only when it is likely to change management or clarify diagnosis—an approach consistent with evidence-based musculoskeletal practice.
One challenge in real-world documentation is terminology variability. Drf Crefito may be recorded differently across clinics or regions, while Crefito may be used as a general label for crepitus. From an expert standpoint, the risk is that different notes may appear to mean the same thing while actually capturing different clinical realities.
To mitigate that, clinicians benefit from standardized narrative templates: even if the label varies, the content of the description remains stable—location, timing, pain association, and functional context. This is especially important for handoffs between primary care, physiotherapy, orthopedics, and radiology.
| Assessment element | Emphasis in Drf Crefito-style documentation | What to check when using Crefito wording |
|---|---|---|
| Core phenomenon | Describe tactile/audible crepitus, not only a label | Clarify whether “Crefito” denotes crepitus vs another sensation |
| Motion phase | Record early/mid/end range and movement direction | Identify whether it consistently appears at the same phase |
| Pain relationship | Document timing of pain relative to crepitus | Specify whether pain precedes, coincides, or follows crepitus |
| Reproducibility | Note consistency across repeated movements | Record if it changes with fatigue, activity, or posture |
| Associated signs | Include swelling, tenderness, stiffness, catching/locking | State which associated symptoms were present or absent |
| Clinical next step | Choose conservative pathway or targeted evaluation based on likelihood | Decide whether imaging or referral adds actionable information |
To keep Drf Crefito and Crefito-related documentation safe and clinically useful, the following conditions are recommended:
Below is a practical, step-by-step guide that aligns with expert documentation standards for crepitus assessment (including how Drf Crefito is often operationalized).
For many musculoskeletal presentations where Crefito is observed, conservative care may be appropriate—especially when there is no evidence of emergent pathology. The clinician’s decision should be driven by symptom severity, function loss, and exam findings rather than the sound itself.
From an industry and practice-management perspective, high-quality conservative pathways often include:
It’s also important to document what conservative strategies were tried and the patient response, so Drf Crefito-style notes remain clinically actionable over time.
To keep discussion evidence-aligned, background perspectives in this guide are consistent with widely used clinical principles and guidance in musculoskeletal care. When referencing general standards (such as cautious imaging selection and comprehensive assessment), the approach reflects established positions in peer-reviewed and health-system guidance. For readers who want formal reference points, standard sources include:
Note: If you share your region or intended clinical setting, I can suggest specific local guideline titles and the very relevant sections for crepitus-related assessment and documentation.
“Crefito” is commonly used to describe crepitus—audible or palpable crackling/grinding sensations during joint movement. Clinically, it is very useful when linked to pain, range-of-motion changes, swelling, or functional limitation.
In very care settings, Drf Crefito functions more like a documentation and assessment framework rather than a single diagnosis. It emphasizes how clinicians record crepitus characteristics and correlate them with symptoms and exam findings.
No. Crepitus can occur in a range of conditions and may also be present without serious pathology. Clinical significance depends on associated symptoms, exam results, and changes over time—not on the sound alone.
Imaging is generally considered when results are likely to change management, when there are concerning features (e.g., significant trauma, suspected inflammatory disease, or progressive neurologic issues), or when symptoms persist despite appropriate conservative treatment. This aligns with imaging stewardship principles used across musculoskeletal care.
A strong note should include: joint location, movement phase (early/mid/end range), whether crepitus is audible/tactile, pain timing relative to the phenomenon, range-of-motion metrics, and any associated signs such as tenderness, effusion, stiffness duration, or locking.
Patients can describe: when the crepitus occurs (during stairs, squatting, overhead reaching), whether it hurts, whether it is improving or worsening, and whether they feel catching or instability. Short, specific examples often improve diagnostic clarity.
Yes. Seek urgent evaluation if there is severe trauma, fever with joint symptoms, rapidly progressive swelling, unexplained systemic symptoms, inability to bear weight in sudden onset cases, or signs suggesting infection or serious inflammatory conditions.
Often, yes—when the underlying driver is addressed (for example, mechanical overload, muscle imbalance, or movement-control deficits). Rehabilitation plans should be individualized and reassessed based on symptom response and functional outcomes.
Properly applied, Drf Crefito and Crefito-related assessment practices can raise the quality of musculoskeletal care by turning a vague report (“it cracks”) into a clear clinical observation that supports better differential thinking and more consistent follow-up. The central principle is simple and objective: document crepitus as a measurable phenomenon, then interpret it in the full clinical picture.
If you tell me the target joint (knee, elbow, shoulder, or another region) and the intended audience (clinician, student, patient education, or clinic SOP), I can tailor the workflow, FAQs, and documentation template structure accordingly.
A key reason clinicians adopt frameworks like Drf Crefito is that joint crepitus often enters clinical conversations in an informal way—patients mention “crackling,” clinicians feel a vibration or hear a sound, and the episode is quickly categorized as “normal aging” or “cartilage wear” without further unpacking. While such assumptions may be sometimes correct, they often ignore the nuance that makes crepitus clinically actionable: the pattern of when it occurs and how it behaves with movement, pain, swelling, and functional tasks.
When documentation is inconsistent, two clinicians can examine the same patient and reach divergent impressions—not because one is less competent, but because they captured different aspects of the phenomenon. One might record “crepitus present” without specifying phase, side, or pain association. Another might record “tactile crepitus with knee extension, end range, with pain 4/10” and also note effusion or impaired tracking. A third clinician reading the notes later may interpret these as different clinical pictures. The “value” of Drf Crefito is not that it replaces clinical reasoning; rather, it encourages the documentation habits that preserve that reasoning for future decisions.
Because terminology can vary, one of the first quality steps is to clarify what sensation is being described. Patients sometimes report “crackling,” “popping,” “snapping,” “clicking,” “grinding,” “bubbling,” or even “tightness with movement.” Clinicians then need to determine whether the sensation aligns with crepitus (audible/tactile irregularity related to movement of articular or periarticular structures), or whether it is more consistent with:
This distinction matters because it changes the differential diagnosis and the urgency of workup. A structured Drf Crefito note should therefore not only state that crepitus occurred, but also describe its behavior in a way that others can reproduce and compare.
In a high-quality assessment, “observe” includes several sub-elements:
The observation step is where Drf Crefito becomes most practical, because it sets up the subsequent quantification and correlation. If the observation is vague, the quantification and correlation become guesswork.
Clinicians often hesitate to quantify crepitus because it seems too subjective. Yet quantification is still possible through consistent documentation strategies that do not require expensive equipment.
Examples of clinically usable quantification include:
Quantification doesn’t need to be perfect; it needs to be consistent. When notes include consistent quantification, care teams can track changes over time. For instance, a clinician can later determine whether rehabilitation reduced pain but crepitus persisted, or whether both improved together—each pattern suggests different underlying mechanisms and different expectations for prognosis.
The correlation step is often underestimated because it sounds like “ask more questions.” But when correlation is done systematically, it becomes a tool for narrowing differential diagnosis.
One correlation approach aligned with Drf Crefito documentation is to ask questions in a sequence that links crepitus to symptoms and mechanics:
These questions align with how evidence-based clinicians build a differential diagnosis: they evaluate whether symptoms fit inflammatory, degenerative, post-traumatic, or purely mechanical drivers. Crepitus is then interpreted through that lens.
Management decisions should rarely hinge solely on whether crepitus is present. Instead, Drf Crefito supports planning by encouraging clinicians to identify the probability that crepitus represents:
Even if imaging is not immediately pursued, the plan can include conservative strategies targeted to the suspected mechanism. For example, if crepitus is strongly linked to patellofemoral movement and occurs during loaded knee flexion, strengthening of hip and quadriceps control and movement retraining may be prioritized. If crepitus is paired with swelling and end-range pain, clinicians might increase focus on controlling inflammatory response and load management, and consider time-based reevaluation.
Many care teams operate with inconsistent documentation styles. A key implementation challenge for frameworks like Drf Crefito is training and standardization: one therapist may record “crepitus,” another “cracking,” another “grinding,” and another “crepitus noted.” The SOP solution is to standardize the fields rather than the label.
A practical clinic documentation SOP could require that every crepitus note includes:
When fields are standardized, the clinical meaning of the note remains stable even when terminology varies. This is how Drf Crefito improves communication across disciplines.
Even well-intentioned clinicians can commit diagnostic or documentation errors. A Drf Crefito-informed approach encourages awareness of these pitfalls:
By explicitly addressing these pitfalls, teams can use Drf Crefito as a safety and quality tool rather than merely an acronym.
Crepitus occurs across many joints. However, the way clinicians assess it and what they prioritize differs by region due to anatomy and common pathologies. Below are practical examples showing how a Drf Crefito-style note can adapt while maintaining the same framework.
In knee assessment, clinicians commonly distinguish patellofemoral crepitus (often associated with pain during stairs, squatting, or prolonged sitting) from tibiofemoral joint-line crepitus. A Drf Crefito-informed note could include:
These details help determine whether the likely driver is maltracking and load control (which responds well to targeted rehab), degenerative change (where symptom management and strength/endurance are crucial), or structural injury requiring further evaluation.
Shoulder crepitus can come from multiple sources: glenohumeral joint surfaces, subacromial region, or scapulothoracic mechanics. A clinician should document:
In a Drf Crefito approach, the goal is to avoid oversimplifying shoulder crepitus into “arthritis.” Instead, the note should specify the movement context and whether there are accompanying functional deficits that rehab can target.
Elbow crepitus often appears in contexts involving tendon irritation, repetitive loading, or post-traumatic changes. Documentation should include:
This information helps the care team decide whether to prioritize tendon-focused rehab, mobility and mechanics training, or further evaluation if structural concerns are suspected.
Sometimes patients use “creaking” language to describe sensations that originate in hip joint structures, labrum-related issues, iliopsoas region, or even lumbar movement. A Drf Crefito note should therefore document:
Without that localization and mechanistic coherence, clinicians may misattribute symptoms. The framework helps enforce localization and correlation.
Assessment is not a single moment; it is a dynamic process. Drf Crefito supports high-quality care by emphasizing reassessment—comparing whether crepitus characteristics change in parallel with pain and function.
A reassessment plan can include:
By building this into the care pathway, clinicians transform crepitus documentation into a longitudinal monitoring tool.
A major clinical value of documenting crepitus correctly is communicating with patients effectively. Patients often hear “cracking” and assume it means “damage is happening right now.” In reality, crepitus can occur for multiple reasons and may not always represent active degeneration. However, if crepitus is paired with pain, swelling, and reduced function, it can reflect an underlying issue that requires attention.
Education messaging aligned with Drf Crefito can include:
When education is aligned with documentation, patients are more likely to adhere to treatment and perceive care as coherent and evidence-based.
While general conservative management was previously described, a Drf Crefito-informed approach can be more specific by linking rehabilitation emphasis to the crepitus pattern and associated symptoms.
Examples include:
Crucially, these adjustments should be guided by documentation: a clinician should be able to read the note and understand why certain rehab choices were made. This is one of the core practical outcomes that Drf Crefito aims to achieve.
Even though imaging may not always be needed, a Drf Crefito-informed note helps justify when imaging or referral is appropriate. Instead of ordering imaging because “crepitus exists,” clinicians order imaging when crepitus is part of a broader pattern that suggests a specific structural concern or when conservative management fails.
Consider imaging/referral when documentation shows:
When imaging is obtained, the note helps radiologists and specialists interpret what they see on imaging in context (e.g., “crepitus audible at end range with pain, localized to patellofemoral region”). This improves the likelihood that imaging results translate into clinical decisions.
To make Drf Crefito truly operational in everyday practice, it helps to use a template structure. The following is an example of what a complete documentation block might look like for a generic joint; it can then be adapted to specific joints and local documentation systems.
Crepitus (Drf Crefito framework):
This template ensures that Drf Crefito notes are more than a label—they become a structured dataset for clinical decision-making.
A useful principle is that benign crepitus tends to be less coupled to pain and dysfunction. Clinically significant crepitus more often appears alongside one or more of the following: persistent pain, effusion, meaningful range limitation, instability/catching, progressive symptoms, and clear mechanistic coherence with the patient’s complaint. In documentation, this means “crepitus present” is insufficient; clinicians should record pain coupling, functional impact, and associated exam signs.
When feasible, yes—especially in joints where age-related crepitus is common. Comparing helps identify whether the crepitus is likely incidental or uniquely pronounced in the symptomatic joint. That said, some conditions can be unilateral and clearly symptomatic; comparison should not delay careful assessment when red flags exist.
In that scenario, crepitus may still be meaningful if it correlates with functional limitations, reduced performance, or other subtle findings. If symptoms are absent and exam reveals no functional impairment or concerning signs, clinicians can often proceed with patient education, monitoring, and general physical activity advice rather than aggressive interventions.
Inconsistency does not automatically mean the finding is false; it may reflect variation in load, fatigue, movement technique, or day-to-day symptom fluctuation. A Drf Crefito approach would document the inconsistency (e.g., “crepitus not reproduced in 2 of 5 trials today”) and correlate it with factors such as activity level before the visit, current pain state, and movement speed. This improves note integrity and helps the differential remain accurate.
Yes. Pain and function can improve due to changes in strength, mobility, movement control, and inflammation even if structural changes seen on imaging remain stable. Therefore, care teams should not interpret persistence of crepitus as failure if symptom and function outcomes improve. A longitudinal Drf Crefito note helps track these patterns objectively.
No. Crepitus is a mechanical phenomenon that can arise from joint surfaces, cartilage mechanics, tendon friction, or movement patterns. It may be associated with degeneration in some cases, but it can also be present without ongoing tissue damage. The clinical meaning depends on symptom correlation, functional impact, and progression over time.
If the patient reports crepitus but the clinician cannot reproduce it, documentation should reflect that accurately. For example: “Patient reports audible crackling during stairs; today crepitus not reproduced on standardized test; pain response and ROM assessed.” This maintains honesty in clinical documentation and helps guide follow-up—possibly adjusting test conditions (load, speed, position) during reassessment.
Yes, as long as the scale is used consistently and defined clearly within the clinic. Some clinics define intensity based on whether crepitus is audible in a quiet room versus only tactile, or based on correlation with pain. The key is that the scale should be operational and reproducible so different clinicians interpret it similarly.
Adopting Drf Crefito as a documentation framework may encounter real-world constraints: time limits, variable training, and inconsistent electronic health record templates. Several practical solutions can help.
These solutions keep Drf Crefito from becoming another acronym that exists only on paper. Instead, it becomes a practical system for quality improvement.
While red flags were already listed in general terms, clinicians often benefit from explicitly documenting safety net criteria. A Drf Crefito-informed workflow should include patient-facing escalation guidance, such as when to return urgently.
Examples of safety net language clinicians might document include:
Documenting escalation criteria supports shared decision-making and reduces the risk of delayed care.
Properly applied, Drf Crefito and Crefito-related assessment practices can raise the quality of musculoskeletal care by turning a vague report (“it cracks”) into a clear clinical observation that supports better differential thinking and more consistent follow-up. The central principle is simple and objective: document crepitus as a measurable phenomenon, then interpret it in the full clinical picture.
If you tell me the target joint (knee, elbow, shoulder, or another region) and the intended audience (clinician, student, patient education, or clinic SOP), I can tailor the workflow, FAQs, and documentation template structure accordingly.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You

Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans
Finding an optimal mix of insurance premiums and direct medical costs is crucial for effective healthcare budgeting. This discussion will delve into tactics to achieve a balance that aligns with your finances.
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!
Selecting an adept dentist is critical for ensuring the efficacy and your satisfaction during a dental implant procedure. This in-depth guide is designed to assist you in finding a dental expert who meets your personal requirements, guaranteeing that your path to dental implant success is seamless and fruitful.
Protect Your Perfect Smile: Master the Art of Defending Your Teeth Against Acid Attacks
Though they may tantalize the palate and invigorate the senses, foods and drinks with high acid content are a double-edged sword with regard to oral wellness. Continual exposure to these substances progressively strips away the protective enamel from our teeth, which can lead to increased sensitivity, changes in coloration, and a variety of other dental complications. This composition offers insight into relishing these zesty favorites while safeguarding your teeth from damage.

Discovering Heartis Eagle Mountain
Heartis Eagle Mountain is a prominent senior living community that offers a range of services and amenities aimed at enhancing the quality of life for its residents. Situated in a peaceful setting, it combines exceptional care with engaging activities, providing a holistic environment that caters to seniors' physical, emotional, and social needs.

Unveiling the Top Dental Implant Options for Seniors: Transform Your Smile with the Ultimate Guide to Restored Radiance
The significance of oral health cannot be understated for the elderly population as they are commonly afflicted with tooth loss due to a multitude of factors, including decay and gum disease. Dental implants have risen to prominence as a prime method of teeth replacement, acclaimed for their long-lasting nature, functional prowess, and striking similarity to our own teeth. This discussion delves deeply into the realm of dental implants to demonstrate why they are considered the optimal choice for aged individuals aiming to enhance their smiles and overall life quality.

Boost Your Defenses: 20 Proven Strategies for a Stronger Immune System
Having a robust immune system is essential to protect our bodies from harmful microorganisms and preserve our general health. Although some elements that affect our immunity are out of our hands, many lifestyle decisions can help us enhance our immune defenses naturally. This piece delves into 20 practical methods to empower your immune system, increasing your capacity to ward off diseases and sicknesses.
